What Is Normal Anion Gap Metabolic Acidosis?
Normal anion gap metabolic acidosis is an acid-base imbalance in which the blood becomes acidic because bicarbonate is depleted or not properly regenerated, but the anion gap stays within the expected limits. It is also commonly called hyperchloremic metabolic acidosis or non-anion gap acidosis, because the drop in bicarbonate is typically accompanied by a rise in chloride.
In metabolic acidosis, the body has excess acid or too little base. In the normal anion gap form, the main issue is usually bicarbonate loss rather than accumulation of unmeasured acids. That is why the pattern often includes a low serum bicarbonate and increased chloride, while the calculated anion gap remains normal. This pattern can develop from gastrointestinal loss, kidney dysfunction, or medication effects.
The clinical presentation may include rapid breathing from compensatory respiration, fatigue, weakness, nausea, or signs of an electrolyte imbalance. Recognizing the pattern matters because the diagnostic approach differs from that used for high anion gap acidosis. A focused laboratory evaluation can help identify whether the cause is in the gut, the kidney, or another source of bicarbonate loss.
In what way an Anion Gap Calculator Aids in Acid-Base Assessment
An anion gap calculator is a practical tool for acid-base assessment because it enables clinicians read basic chemistry values in perspective. The calculator takes sodium, chloride, and bicarbonate values from serum electrolytes to estimate the anion gap and see whether the acidosis is likely a normal gap pattern or a high gap pattern.
In a common formula, sodium is weighed against chloride and bicarbonate. When chloride rises as bicarbonate falls, the gap may remain normal, pointing toward hyperchloremic acidosis. This pattern can be very helpful when the cause is not obvious from the clinical presentation. A calculator does not substitute for clinical judgment, but it supports a systematic diagnostic approach.
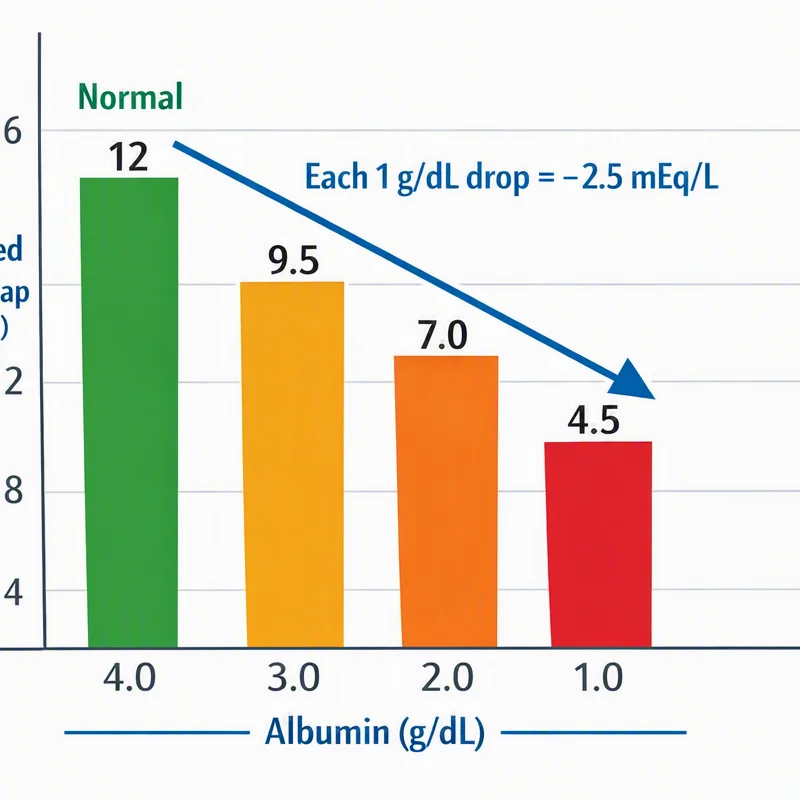
Using an anion gap calculator also enables clinicians avoid missing mixed disorders. For example, a patient may have metabolic acidosis with albumin changes that affect interpretation of the anion gap. Because albumin contributes to the measured gap, low albumin can make a high-gap problem look less significant than it truly is. That is why the anion gap should always be interpreted with the full chemistry panel and the rest of the acid-base picture.
In practice, the calculator can direct the next steps: if the gap is normal and chloride is elevated, the likely issue is often bicarbonate loss, impaired renal acidification, or another cause of chloride retention. That refines the search and improves the efficiency of the workup.
The Primary Reasons of normal anion gap metabolic acidosis
The leading reasons of normal anion gap metabolic acidosis are conditions that decrease serum bicarbonate without producing a large burden of unmeasured acids. The primary mechanisms include diarrhea and other gastrointestinal causes of bicarbonate loss from the gut, renal tubular acidosis, and medication or toxin exposure. Many of these disorders lead to chloride increase because chloride rises as bicarbonate falls.
Recognizing the mechanism helps structure the differential diagnosis. If bicarbonate is lost through the gut, the kidneys usually respond by increasing acid excretion. If the kidneys are the problem, urinary acidification is impaired, and bicarbonate may be wasted or not regenerated appropriately. Medication and toxin causes can affect renal handling of acid and electrolytes, producing a similar lab pattern.
When reviewing the differential, it helps to think in terms of cause: GI losses, kidney tubular defects, or exogenous exposures. Each can produce a similar chemistry pattern, but the associated clues often differ enough to point toward the correct diagnosis.
Gastrointestinal Causes
Diarrhea is one of the most frequent causes of normal anion gap metabolic acidosis. The gut contains bicarbonate-rich fluid, so ongoing stool losses can lead to significant bicarbonate loss. This is a classic example of gastrointestinal loss causing hyperchloremic metabolic acidosis.
An ileostomy can also cause bicarbonate depletion, especially when output is high. Similarly, a pancreatic fistula can drain bicarbonate-rich secretions and contribute to acidosis. These conditions are often recognized by the history: increased output, dehydration, weight loss, or evidence of fluid depletion.
In gastrointestinal causes, the kidneys are usually functioning normally and respond by conserving bicarbonate and increasing urinary acid excretion. That distinction becomes important when interpreting the urine anion gap later in the evaluation. If the kidneys are responding appropriately, the urinary pattern typically reflects increased ammonium excretion.
Kidney-Related Causes
Renal tubular acidosis is a significant kidney-related reason of normal anion gap metabolic acidosis. In this set of conditions, the kidneys have difficulty making acidic the urine or managing bicarbonate properly. The result is a persistent acid-base disorder even when the glomerular filtration rate may be mostly preserved early on.
Type 1 renal tubular acidosis, also called distal renal tubular acidosis, occurs when the distal tubule cannot properly release hydrogen ions. This reduces renal acidification, leading to acid retention and often a increased urine pH. Patients may also develop low potassium and issues related to chronic acidosis.
Type 2 renal tubular acidosis, or proximal renal tubular acidosis, involves the proximal tubule and is commonly associated with bicarbonate wasting. The proximal tubule fails to reabsorb filtered bicarbonate effectively, so bicarbonate is lost in the urine until a new steady state is reached. This can cause chronic metabolic acidosis and may be associated with other proximal tubular defects.
Type 4 renal tubular acidosis is different because it is often linked to impaired aldosterone activity or resistance. It is often associated with hyperkalemia and reduced ammonium production, which leads to impaired acid excretion. When potassium is elevated or inappropriately normal in the setting of acidosis, type 4 disease should be considered.
These renal causes reflect real kidney dysfunction at the tubular level, even when other parts of the kidney may appear relatively preserved. The pattern can be subtle, so blood and urine studies are often needed to distinguish renal tubular defects from GI causes.
Medication and Toxin Causes
Some medications and toxins can produce normal anion gap metabolic acidosis by interfering with renal handling of bicarbonate or acid. Acetazolamide is a classic medication cause because it inhibits carbonic anhydrase in the proximal tubule, leading to bicarbonate loss and producing a hyperchloremic pattern.
Amphotericin B can harm renal tubules and disrupt acidification, sometimes causing renal tubular dysfunction and electrolyte problems. The result may resemble a renal tubular acidosis pattern with low bicarbonate and abnormalities in potassium and other electrolytes.
Toluene exposure is another important toxin-related cause. It can create complex acid-base changes and may present with a normal anion gap pattern, especially when chloride rises as bicarbonate falls. A careful exposure history is essential because the lab pattern alone may not reveal the source.
Medication and toxin causes are often overlooked unless the diagnostic approach includes a detailed review of prescriptions, over-the-counter agents, occupational exposures, and substance use. In the right context, these causes should be near the top of the differential.
How to Differentiate Typical Anion Gap from Elevated Anion Gap Acidosis
Differentiating normal anion gap metabolic acidosis from high anion gap acidosis is one of the key steps in interpreting acid-base status. In normal gap acidosis, the main pattern is usually decreased bicarbonate with higher chloride, resulting in hyperchloremic acidosis. In elevated gap disorders, hidden acids accumulate and increase the gap.
Causes of a high anion gap include lactic acidosis and ketosis. These states add acidic byproducts to the blood, so the bicarbonate decreases without the same matching rise in chloride. That creates a widened anion gap rather than a normal one. When you see a low bicarbonate level, checking the anion gap helps determine whether the problem is loss of buffer or acid accumulation.
Albumin matters here because it is a important unmeasured anion. Low albumin can decrease the expected anion gap and hide a high-gap process. That means a patient with significant lactic acidosis or ketosis may look like they have a less striking gap if the albumin is reduced. Interpreting the chemistry panel https://anion-gap-values582.quantlynix.com/posts/anion-gap-calculator-based-on-serum-chloride without considering albumin can lead to incorrect classification.
A practical diagnostic strategy is to review the serum bicarbonate, calculate the anion gap, and then decide whether the picture suggests a normal gap or high gap disorder. If the anion gap is normal and chloride is high, think of hyperchloremic metabolic acidosis. If the gap is elevated, look for lactic acidosis, ketosis, toxins, renal failure, or mixed disorders. This is where an anion gap calculator is especially helpful as part of the broader evaluation.
Main Diagnostic Observations and Clinical Clues
The key clues in normal anion gap metabolic acidosis come from combining blood chemistry, urine testing, and the overall clinical picture. An arterial blood gas verifies acidemia and helps evaluate respiratory compensation. Serum studies show low bicarbonate, and the chemistry panel often reveals elevated serum chloride.
The urine anion gap is especially helpful when trying to separate GI bicarbonate loss from renal causes. A negative urine anion gap often points to appropriate ammonium excretion, which is more consistent with diarrhea or another GI source. A positive or inappropriately nonnegative value can indicate impaired urinary ammonium excretion, which points more toward renal tubular acidosis.
Potassium levels also give important clues. Low potassium may be seen with diarrhea, type 1 renal tubular acidosis, and type 2 renal tubular acidosis. High potassium is more suggestive of type 4 renal tubular acidosis. Because potassium shifts affect symptoms and treatment, it should always be reviewed alongside bicarbonate and chloride.
Clues from the history are just as important as the laboratory evaluation. Ongoing stool losses, an ileostomy, a pancreatic fistula, recent use of acetazolamide, exposure to amphotericin B, or inhalational exposure to toluene can quickly narrow the cause. A careful diagnostic approach ties together the acid-base pattern, the medication list, and the patient's volume status.
When to Seek Further Medical Evaluation
Additional medical evaluation matters when acidosis is persistent, not explained, or associated with concerning symptoms. Persistent acidosis can suggest ongoing bicarbonate loss, unresolved renal tubular dysfunction, or a chronic disorder that needs focused treatment. Repeated abnormalities should not be overlooked as temporary.
Anyone with suspected kidney disease should be assessed more carefully, especially if the acid-base disorder is accompanied by abnormal creatinine, reduced urine concentrating ability, or changes in potassium. Tubular disorders may appear before major changes in overall kidney function, so early recognition matters.
An obvious electrolyte imbalance or signs of dehydration should warrant prompt attention. Volume depletion can worsen acid-base disorders and make symptoms more severe. Weakness, lightheadedness, confusion, palpitations, or severe diarrhea are all reasons to obtain timely evaluation.
Because normal anion gap metabolic acidosis has multiple causes, follow-up testing may include repeat serum electrolytes, urine studies, and a more detailed look at medications and exposures. The goal is to identify the source of bicarbonate loss and address the underlying problem, not just the abnormal lab value.
Frequently Asked Questions
What defines normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is a type of acid-base disorder in which the blood bicarbonate level is low, but the anion gap stays within the normal range. It is often called hyperchloremic metabolic acidosis because chloride rises as bicarbonate falls. Common causes include diarrhea, renal tubular acidosis, and certain medications.
Which are the most common causes of normal anion gap metabolic acidosis?
The most common causes are loose stools and other forms of intestinal bicarbonate loss, tubular acidosis, and medication or toxin exposure. Examples include ileostomy, pancreatic fistula, acetazolamide, amphotericin B, and toluene.
How can an anion gap calculator help diagnose acidosis?
An anion gap calculator uses Na, chloride, and bicarbonate values from serum electrolytes to determine whether the acidosis is a normal anion gap or high gap disorder. This helps shape the diagnostic approach and can point toward hyperchloremic acidosis, lactic acidosis, ketosis, or mixed patterns.
Why can diarrhea cause normal anion gap metabolic acidosis?
Loose stools can cause normal anion gap metabolic acidosis because stool contains bicarbonate. When the body loses bicarbonate through the intestines, serum bicarbonate falls and chloride rises to maintain electrical balance. This produces a classic chloride-rich pattern with a normal anion gap.
Which lab tests help distinguish renal tubular acidosis from other causes?
Helpful tests include an blood gas analysis, serum electrolytes, potassium, Cl level, and the urine anion gap. These results help determine whether the problem is due to GI bicarbonate loss or impaired renal acidification from tubular acidosis. Albumin should also be considered when interpreting the anion gap.