How the Anion Gap Assesses
The anion gap is a useful part of acid-base evaluation because it enables medical professionals and students see how the main electrolytes relate to one another in the blood. It is not a literal measurement of a single substance. Instead, it is a calculated value derived from standard serum chemistry tests that shows the relationship between measured cations and measured anions.
In practical terms, the anion gap can help identify whether a patient has an acid-base disorder, especially metabolic acidosis. When the body accumulates acids or reduces bicarbonate, the chemistry panel changes in expected ways. An elevated or unexpected gap can point toward hidden acids, also called unmeasured anions, that are not directly listed on a standard electrolyte panel.
The most relevant measured values in this calculation are sodium, chloride, and bicarbonate. Some formulas also include potassium, though many clinical settings exclude it for simplicity. Because the result is derived from routine serum electrolytes and other blood chemistry data, the anion gap serves as a efficient diagnostic tool during patient assessment.
An Anion Gap Calculator makes it simpler to calculate anion gap values efficiently and reliably. That can support a more precise understanding of the cause of acidosis, whether the issue is a simple bicarbonate loss, an excess acid load, or another process affecting the body’s acid-base balance.
How to Use the Anion Gap Calculator
To use an Anion Gap Calculator, input the serum values for sodium, chloride, and bicarbonate from the lab results. These values are usually reported in milliequivalents per liter, and the calculator applies the standard formula to produce the result.
Most calculator tools are designed for quick bedside review or educational use. They allow convert a basic blood chemistry panel into a more meaningful metabolic acidosis evaluation. If you also have the albumin level available, a more advanced calculator may let you correct for albumin and produce a corrected anion gap.
Here is the usual process:
- Input the sodium value from the lab report. Add chloride and bicarbonate values from the same sample if possible. If needed: add potassium if the calculator includes it. As an option: input albumin if you want a corrected value. Compare the result against the expected reference range or normal range.
For reliable interpretation, the numbers should come from the same blood draw whenever possible. Changes in timing, fluid status, or treatment can affect the result. The calculator is most useful when paired with the rest of the clinical picture rather than used as a standalone answer.
Anion Gap Formula and Computing Stages
The most common anion gap formula can be written as:
Na minus Cl minus HCO3
Written out, this means:
Anion gap = sodium - chloride - bicarbonate
Some practitioners include potassium in the equation:
Anion gap = sodium + potassium - chloride - bicarbonate
This method may give a slightly higher result, but both approaches are used in practice. What matters is to know which method the calculator is using so the interpretation matches the calculation.
To determine the value stepwise:
- Start with the sodium value. Subtract chloride. Subtract bicarbonate. If potassium is part of the formula, add potassium before subtracting chloride and bicarbonate.
Calculation example: With sodium at 140, chloride equals 102, and bicarbonate is 24, the calculation would be 140 - 102 - 24 = 14. If potassium is also included at 4, then 140 + 4 - 102 - 24 = 18.
This simple arithmetic can help identify an elevated anion gap, but interpretation depends on the lab’s techniques and the patient’s overall status. A result that seems abnormal should always be considered in the setting of clinical symptoms, medications, and other lab results.
Normal Anion Gap versus Increased Anion Gap
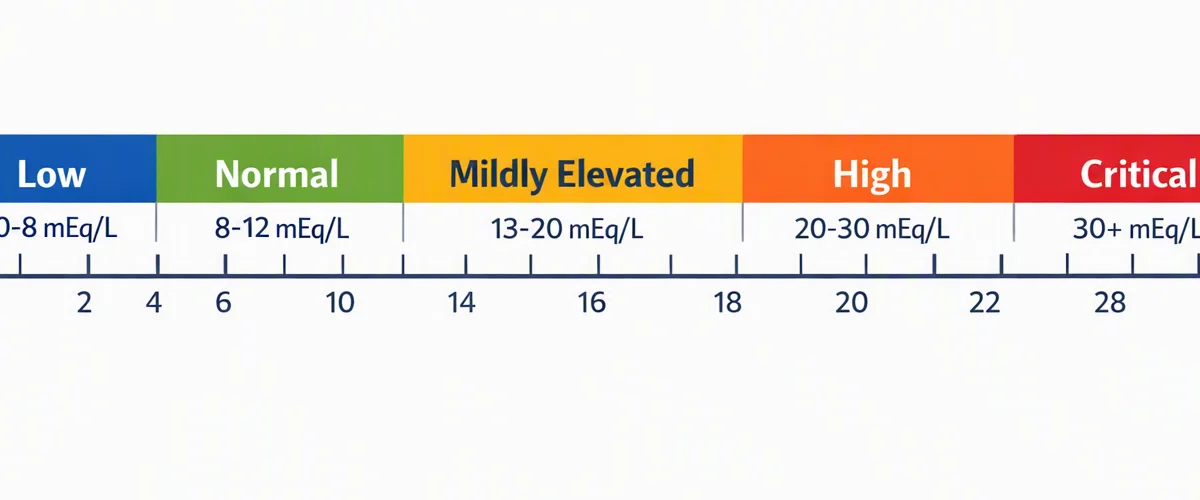
A standard anion gap usually suggests that the balance between measured cations and anions is inside the expected normal range. That does not automatically imply the patient is normal, but it may suggest that the acidosis, if present, is due to bicarbonate loss rather than accumulation of unmeasured acids.
A high anion gap is more concerning because it often points to the presence of extra acids in the bloodstream. This pattern is classically seen in high anion gap metabolic acidosis, where acids accumulate and bicarbonate falls as the body tries to counteract the acid load.
Recognizing the difference is central to metabolic acidosis workup. A normal gap can be associated with diarrhea, renal tubular issues, or bicarbonate loss. A high gap more often suggests hidden acid accumulation from conditions such as lactic acidosis, ketoacidosis, or kidney-related causes.
The anion gap is not a diagnosis by itself. It is a clue. The result should direct additional testing and support broader clinical reasoning rather than substitute for it.
Corrected Anion Gap & Albumin Calculation
Albumin is a significant unmeasured anion in blood, so decreased albumin can make the measured gap look lower than it really is. This is why many of the clinicians use a corrected anion gap when hypoalbuminemia is present.
If albumin is low, the usual gap may underestimate the severity of an acid-base problem. In that situation, the calculator may correct for albumin to more clearly reflect the underlying chemistry. This adjustment is especially helpful when interpreting lab results in very sick patients or anyone with low protein levels.
Why does this matter? A patient can appear to have a typical anion gap even when excess acids are present if albumin is low enough. The corrected result can reveal a concealed high anion gap that would otherwise be missed.
Albumin adjustment improves clinical interpretation because it accounts for one of the key contributors to the body’s electrical balance. In practice, corrected values are often more informative than the raw number alone, especially when evaluating suspected acid-base disturbances.
Common Causes of Elevated Anion Gap
An high anion gap usually means that the body has collected acids or other unmeasured charged substances. Various conditions are classically associated with this pattern, and recognizing them helps narrow the source of acidosis.
Lactic acid buildup is among the most frequent causes. It occurs when lactate builds up due to poor oxygen delivery, shock, severe illness, or other physiologic stress states. Because lactate is an unmeasured anion, it increases the gap.
Acid buildup from ketones is another important cause. This may occur in diabetes, starvation, or alcohol-related states, where ketone bodies collect and disrupt the acid-base balance.
Uremia from reduced kidney function is also important. In severe renal failure, acids are not cleared effectively, and retained toxins add to a higher gap.
Other causes can include toxins, medications, and metabolic conditions that promote acid formation or reduce acid removal. The main point is that a high gap should prompt a search for unrecognized acid buildup or poor clearance rather than a narrow focus on the number itself.
How to Understand Results in Medical Context
Reading the anion gap correctly requires far more than a number. A good clinical interpretation brings together the gap with symptoms, clinical markers, history, medications, and other lab values such as an arterial blood gas.
The arterial blood gas helps show whether the patient actually has low pH or high pH, whether compensation is occurring, and whether the primary disorder matches the chemistry panel. The anion gap then brings another layer by identifying whether the metabolic problem is likely due to added acids or bicarbonate loss.
The delta gap is also valuable in more complex cases. It contrasts the change in the anion gap with the change in bicarbonate to look for mixed disorders. For example, a patient may have high gap metabolic acidosis along with a separate metabolic alkalosis or a concurrent normal gap acidosis.
This is why the Anion Gap Calculator is best used as part of a broader workflow. It aids decision-making, but the final interpretation should include the complete acid-base picture, including the patient’s clinical status and any possible base deficit.
Limitations of Anion Gap Calculation
Although the anion gap is helpful, it has several limitations. One issue is lab variation. Different instruments, assay methods, and reporting practices can create slightly different results, which means the reference range may differ by laboratory.
Another limitation is that the gap only reflects measured and unmeasured anions indirectly. It does not identify the specific acid responsible. A high value may suggest a disorder, but it cannot distinguish between lactic acidosis, ketoacidosis, or other causes without additional context.
Electrolyte measurement problems can also affect accuracy. Severe electrolyte disorders, changes in protein concentration, or unusual blood chemistry patterns may distort the result. In addition, the presence of certain ions can change how the gap appears even if the true acid burden has not changed dramatically.
Because of these limits, the anion gap should be used as a component of a thorough acid-base disorder review. It is a helpful clue, but not a conclusive result. The ideal use of the calculator is to guide thoughtful interpretation of lab results, not to take the place of clinical reasoning.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An Anion Gap Calculator is used to calculate anion gap values from routine lab results and help with acid-base evaluation. It is especially useful in metabolic acidosis evaluation because it can help identify whether the problem is related to hidden acids, bicarbonate loss, or another acid-base disorder.
What is the normal anion gap range?
The reference range for the normal anion gap differs by laboratory and by whether potassium is included in the formula. In general, many labs classify a value in the low to mid-teens to be normal, but the exact range should always be interpreted using the reporting lab’s stated normal range.
How do you calculate the anion gap from lab values?
Use the standard anion gap formula: sodium - chloride - bicarbonate. Some versions add potassium before subtracting chloride and bicarbonate. The calculator performs this step directly using the provided serum electrolytes, making it easier to review blood chemistry results quickly.
Why do you correct the anion gap for albumin?
https://anion-gap-help734.huicopper.com/how-to-use-an-anion-gap-calculator-for-hyperchloremic-acidosisYou correct for albumin because low albumin can mask a true gap elevation. In hypoalbuminemia, the measured value may appear normal even when unmeasured acids are present. A corrected anion gap gives a more accurate picture of the patient’s acid-base status.
What conditions cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and uremia. Severe renal failure, toxins, and other causes of retained acids can also cause an elevated value. The result should always be reviewed in the context of the full clinical picture and any associated arterial blood gas findings.